Precision Attachment Denture: Clasps, Locators & Frameworks
Choosing a retention strategy for a removable partial denture comes down to a short list of decisions: clasp or precision attachment, which attachment system, what framework material, and where quality gets verified. Get those right and the prosthesis holds, looks acceptable to the patient, and stays repairable. Get them wrong and you are into a remake cycle.
Key decision points:
- Clasp types, when each one earns its place, and what triggers a remake
- Intracoronal vs. extracoronal attachments, ball/stud, Locator, bar, and magnetic systems
- Framework material and design — Co-Cr, titanium, flexible resin, connectors, rests
- Acceptance criteria at each verification stage, plus repair and reline options
- Turnaround by case type and what a complete prescription needs to include
Send cases, questions, or a prescription for review to our technicians in Shenzhen.
목차
Dentures with Clasps: Design and Retention
Cast circumferential, wrought-wire, and RPI/RPA assemblies remain the most common retention strategy for tooth-borne partial dentures, and they still account for the bulk of dentures with clasps sent to us each month. A clasp delivers retention, reciprocation, and stabilization without requiring full-coverage preparation on the abutment — and when something does wear out, it is the easiest element to repair or replace.
When to Choose Conventional Clasp-Retained Dentures
- Short-span Class III or IV cases where abutments don’t need full-coverage restorations
- Budget-constrained treatment, or plans that won’t authorize a precision attachment
- Enough buccal undercut is available for clasping — typically 0.25 mm measured on a surveyed cast
- Esthetics rank behind function and economics
Wrought-wire (18-8 stainless or chrome-cobalt wire) clasps flex, so they’re often specified on weaker or periodontally compromised abutments. Cast circumferential clasps (Akers, ring, C clasp) are rigid and need careful surveying; they suit abutments that can tolerate a higher lateral load.
Pooled evidence for cast-clasp partials is favourable. A 2024 review reported a 5-year survival of about 95.1%, with other longitudinal data putting cumulative survival near 96.4% at five years and 89.9% at ten years. That headline figure hides the maintenance load — caries-free rates in the same literature run closer to 58.4% at five years — and periodontal inflammation around abutments remains clinically relevant even when the denture itself survives.
Reducing Visible Metal in Clasp-Retained Dentures
Lingual clasps (RPI, RPA) move the retentive arm entirely to the lingual aspect. For anterior abutments the options narrow considerably: a precision attachment removes the visible clasp altogether, or a polyamide flexible framework hides it by matching tissue colour.
Polyamide frameworks carry real trade-offs. Nylon bonds differently from PMMA, which makes repair, tooth addition, and especially relining harder — a within-subject comparison of clasp-retained partial dentures covers this alongside clasp fracture, tooth wear, and distal-base sinking as the recurring failure modes. Flexible frameworks also lack rigidity, which compromises load distribution.
Common Clasp Denture Problems and Remake Reasons
- Retention too weak (denture dislodges in function) or too tight (patient can’t seat or remove it)
- Clasp tip interfering with centric or lateral occlusion
- Reciprocal arm not contacting, or positioned too far from the retentive terminal
- Clasp arm fracturing during try-in — usually wrong alloy, over-flexure, or an undercut beyond what the material tolerates
Worth knowing: in several reported series the most frequent technical failure is tooth or acrylic fracture, not metal clasp fracture. Framework and clasp fractures accounted for under 5.2% of remakes over observation periods up to ten years.
Precision Attachment Dentures: Types and Applications
A precision attachment is a mechanical retainer other than a conventional clasp. Compared to dentures with clasps, a precision attachment denture delivers higher retention with less visible metal, and many let you replace the worn part without remaking the prosthesis. Each attachment has two parts: a patrix (male) fixed to the abutment or implant, and a matrix (female) held in the denture. Most are prefabricated with close tolerances.
Intracoronal vs Extracoronal Precision Attachments
Intracoronal attachments sit inside the crown contour — key-and-keyway designs. The removable framework carries the male key; the crown holds the female slot. They’re hidden and can give rigid retention with a controlled path of insertion. The cost is significant tooth reduction, high lab precision, and near-parallel abutments. Where the crown is short or the pulpal prognosis is uncertain, the prep may not be advisable.
Extracoronal designs (ERA, ASC, Ceka) mount on the distal or buccal surface of the crown. They’re bulkier and can trap food, but easier to place and to manipulate, and many allow a resilient hinge that lets a distal-extension base move independently rather than levering on the terminal abutment.
The mechanics and case selection for precision attachments are set out in a classic review of attachments for removable partial denture design, with the indication and complication profile detailed in a combined prosthesis case series using extracoronal castable precision attachments.
Locator Denture Attachments vs Ball and Stud Systems
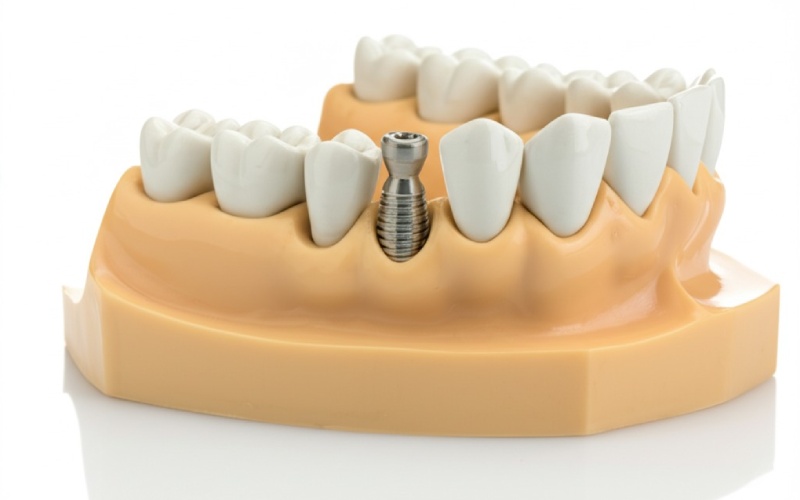
Ball or stud abutments screw into implants or are fabricated onto root copings. The denture houses a metal cap with a replaceable nylon or elastomeric ring that grips the ball. When the ring wears out, it pops out and a new one snaps in — no lab remake.
A locator denture replaces the clasp entirely, which is why it shows up so often in fully edentulous lower-arch cases and in implant-assisted partials where the remaining teeth shouldn’t carry a visible arm. Locator uses a push-button principle at a lower profile, with self-aligning geometry and inserts colour-coded by retention. Legacy Locator inserts are nominally:
| Insert | Colour | Approximate force |
| Extra-light | Blue | 6.67 N ≈ 1.5 lb |
| 빛 | Pink | 13.35 N ≈ 3.0 lb |
| 일반 | 지우기 | 22.24 N ≈ 5.0 lb |
| Extended range | Red / orange / green | Angle-dependent; green commonly reported around 3–4 lb |
Treat those as nominal reference values, not intraoral guarantees — angulation, wear, plaque, insert deformation, housing position, and implant parallelism all shift the real number. An independent in-vitro comparison found initial retention spanning roughly 7.7–19.9 N for a ball system and 3.3–60.2 N for Locator R-Tx, depending on the device tested.
Where ball/stud/Locator fit
- Two-implant mandibular overdenture
- Tooth-supported overdenture on strategically preserved roots
- Implant-assisted partial denture — a Class I with two posterior implants removes the need to clasp the remaining anterior teeth
- Constrained restorative space (low-profile abutments starting around 2.5 mm above tissue)
- Patients who want simple home maintenance and a wear part they can swap
Where it doesn’t fit
- Severe implant divergence (beyond roughly 20–25°) — balls don’t splint and generate uneven force
- Heavy bruxism or parafunction without a protective protocol
- Limited dexterity, where a bar clip is easier to seat than a small cap
On insert service life: wear usually becomes clinically relevant in the first 1–1.5 years, one study reported an attachment/component life of about 22.6 months, and simulated cycling showed a 59–70% drop in retentive force after 18 months. In practice some patients need changes every few months and others go years — recall-based assessment is more defensible than a fixed calendar interval.
Bar-retained overdentures
A bar connects two or more implants or roots into one rigid unit; the denture carries a clip, rider, or sleeve. Bars splint the abutments and distribute load, which helps where ridge support is poor. Common systems include Hader (round bar, cantilevered clip) and Dolder (egg-shaped bar, rider).
Indications: four or more implants; high stability requirement; atrophic ridge with minimal tissue support; a patient who wants maximum retention and accepts the added bulk and hygiene burden.
Contraindications: insufficient restorative space (bar, clip, acrylic, and teeth often need 12–14 mm vertical clearance); limited dexterity or cognitive impairment; budget — bar and clip cases typically run well above ball or Locator fees in published schedules.
Magnetic attachments
Rare-earth magnets can sit in root copings or implant abutments with a matching keeper in the denture. They need almost no insertion path and very little vertical space, but retention is modest — roughly 200–400 g per magnet against ~1,500–3,000 g for a standard Locator insert. Corrosion and gradual strength loss are concerns, and they’re contraindicated in patients with older pacemakers. Use has declined as Locator and low-profile balls improved.
Denture Framework Materials and Design Options
The framework is the metal or high-strength polymer skeleton that connects rests, clasps or attachment housings, major and minor connectors, and the denture base retention mesh. Framework design directly impacts load distribution, patient comfort, speech, and abutment longevity.
Denture Framework Material Selection
Cobalt-chromium (Co-Cr) is the U.S. standard for cast RPD frameworks. High stiffness, thin cross-section (1–1.5 mm for major connectors), decades of handling experience, moderate cost. Castable or millable.
티타늄 (commercially pure or Ti-6Al-4V) is lighter, more biocompatible, and less likely to trigger metal allergy. But harder to cast, with porosity and solder issues. Digital milling is the preferred titanium route. Specified where documented nickel or cobalt sensitivity exists, or when minimal weight matters — a maxillary Kennedy Class I with a long span.
Polyamide flexible frameworks (Valplast, Flexite) use pink or gingiva-toned nylon to hide clasps entirely. They lack rigidity, which leads to poor load distribution, difficulty with occlusal adjustment, and limited reline options. Seen more often as an interim or esthetic-only solution than for long-term chewing function.
Framework Design: Major Connectors, Rests and Minor Connectors
Major connector — the rigid plate or bar that unites both sides. Mandibular designs: lingual bar (half-pear section 4 mm × 2 mm minimum, positioned at least 3 mm below gingival margin), lingual plate (when bar placement is impossible), labial bar (rare; when lingual space unavailable). Maxillary designs: single or double palatal strap, anterior-posterior strap, full or partial palatal plate. Must be rigid enough to distribute force without flexing, thin enough to avoid speech interference, and relief-free over tissue to prevent irritation.
Rests transmit occlusal load onto abutment teeth. The abutment has a prepared rest seat; the framework rest sits there during function. Occlusal rests are standard (round or spoon-shaped, 1.5 mm deep minimum). Cingulum rests sit on the lingual of anterior teeth. Incisal rests on incisal edges are less favourable but may be unavoidable in severe wear. Every abutment should carry a rest to prevent tissue-ward prosthesis movement under load.
Minor connectors join clasps, rests, and indirect retainers to the major connector. They must be rigid, with adequate bulk (usually 2–3 mm, taper smoothly), and positioned to avoid soft-tissue impingement or food traps.
Design errors that lead to remakes: major connector too thin → framework flexes and fractures within months; rest seat not prepped or too shallow → rest floats, denture sinks into tissue; minor connector crosses gingival margin perpendicularly → food and plaque accumulate; inadequate relief over rugae or torus → pressure sore on delivery.
Cast vs CAD/CAM Milled Denture Frameworks
Traditional cast framework: master cast duplication and surveying; wax-up; sprue, invest, burnout, cast in Co-Cr; finish, polish, try-in; process denture teeth and base. Allows complex undercut geometries and is economical for single cases, but introduces shrinkage (≈2%), potential porosity, and longer turnaround since wax-up is manual. Soldering attachments or retention mesh demands careful heat management to avoid distortion.
CAD/CAM milled framework: scan (intraoral or model), design digitally (3Shape, exocad), export to 5-axis mill, mill from Co-Cr or Ti puck, finish and polish, process base. Tighter tolerance (±20–50 µm vs. ±100–200 µm for casting), no wax-up variability, design replication if the patient loses the prosthesis. The workflow tends to be one to two days shorter and the digital file can be archived for remakes. But milling equipment is expensive and some complex clasp geometries — extreme undercuts, wire arms — remain easier to wax-cast.
Denture Quality Control, Repairs and Remakes
Removable work goes through several verification stages: model inspection, framework try-in, wax try-in (teeth set on the framework in wax), and final delivery. Each stage has acceptance criteria; skipping a stage or accepting a borderline fit commonly triggers remakes and patient dissatisfaction.
Framework try-in checkpoints
Before processing acrylic:
- Framework seats fully on the master cast, no rocking or bind
- All rests drop into their seats; no rest bridging across the prep
- Clasps engage abutment undercuts with appropriate retention — firm finger pressure to remove but not damaging
- Reciprocal arms contact the abutment simultaneously with or before retentive terminals engage
- Major connector clears tissue by 0.5–1 mm, doesn’t impinge on frenum or rugae
- Tissue stops and finishing lines are smooth, no sharp edges
Wax try-in
The dentist evaluates occlusion (centric, protrusive, lateral contacts balanced; no premature interference), esthetics (midline, tooth size, shade, incisal edge, smile line), phonetics (S-sounds, F-V, VDO comfortable), and retention (denture stable during functional movements).
This is the last chance to adjust tooth position, plane, or VDO before processing. After processing, changes require cutting teeth off the acrylic base — doable but time-consuming and may compromise base strength.
Final denture inspection
Check for smooth balanced occlusion, well-adapted base, properly engaging clasps or attachments, and polished surfaces free of roughness, bubbles, or voids.
Immediate-remake triggers: air bubbles or porosity in the base (honeycomb appearance on cross-section), base not fully seated on the cast, occlusion severely off from the approved wax try-in, clasp fractured or retention out of spec.
Denture Relining, Repairs and Attachment Replacement
Soft reline (tissue conditioner or permanent soft base) is for sharp ridges, chronic soreness, or severe resorption. Permanent soft liners (silicone-based) last one to two years but may harbour Candida if not cleaned properly.
Hard reline (chairside or lab) replaces the tissue surface with new acrylic while keeping teeth and framework. Indicated where occlusion and esthetics are acceptable but the denture has loosened due to ridge resorption. Lab relines generally fit better than chairside relines because the lab can process under pressure and cure fully.
Denture base fracture: midline fractures are common in thin bases or when the prosthesis is dropped. Repair involves cleaning, bonding agent, autopolymerizing acrylic fill, and recontouring. Repair strength typically reaches 60–80% of the original; fracture-prone dentures should get a metal mesh during the next rework cycle.
Tooth replacement: if a denture tooth fractures or is lost, the lab can bond a new tooth in place with acrylic. The base is roughened, the replacement positioned, acrylic flowed around it, and occlusion adjusted after curing.
Ball/Locator insert replacement: inserts wear over 12–18 months under normal function (faster in bruxers). The metal housing stays; the insert pops out and a new one snaps in. Patients can buy replacement inserts from the lab or swap them chairside in two to three minutes (pop out with the removal tool, snap in the new one, verify retention).
Working with a Dental Lab on Removable Dentures
Required Information for an RPD Lab Prescription
A complete prescription cuts guesswork and reduces remakes:
- Kennedy classification and modification (“Class I mod 1”)
- Abutment teeth and retention type (“clasp #6, #11; precision attachment #3, #14”)
- Rest seat prep status (“rest preps completed” or “no preps, to be placed on model”)
- Major connector design if you have a preference (lingual bar, palatal strap, etc.)
- Attachment type and brand with model number if known (“Locator abutments 3 mm, standard retention”)
- Tooth shade, mold, arrangement preference (photos help)
- Try-in required? (“wax try-in requested” vs. “process to completion”)
- Special instructions (relief over torus, avoid frenum, bar pickup required, etc.)
The number-one source of back-and-forth is missing abutment information or unclear attachment specs. If the prescription says “Locator” without naming abutment height or retention level, the lab has to call. If the abutment analog or a pickup impression is sent with the abutment in place, the lab can duplicate it exactly.
Digital vs Conventional Denture Lab Workflows
Conventional: alginate or PVS preliminary impression; custom tray, border-molded, final impression in PVS or polyether; jaw relation record; master cast poured in die stone.
Digital: intraoral scan of edentulous areas, abutments, and opposing arch; virtual articulation or physical facebow plus bite registration; STL exported; lab prints model or designs directly on the scan.
Digital scans eliminate impression distortion and shipping damage, allow design previews before any physical fabrication, and store the case file permanently for remakes. But scanning large edentulous spans — especially flabby ridges — can be challenging; some labs still request a conventional final impression for tissue-supported areas even when the abutment teeth are scanned digitally.
Frequently Asked Questions About Denture Retention
Can I add a tooth to an existing RPD?
Yes, if the base and clasp are intact. The technician adds a new denture tooth and processes acrylic around it. The framework doesn’t change. Turnaround is typically 3–5 days.
What if the clasp breaks?
Wrought-wire clasps can be replaced by soldering or welding a new arm. Cast clasps are integral to the framework; if a cast clasp arm fractures, the framework usually needs remaking unless laser welding can repair the break.
How long do Locator inserts last?
Under normal function, 12–18 months. Heavy bruxers or high occlusal force may need replacement every 6–9 months. Inserts are inexpensive and user-replaceable; keep a few spares at the office.
Do I need to prepare rest seats before the impression?
Yes. Rest seats should be prepped on abutment teeth (or crowns) before the final impression. If the lab receives a cast with no rest preps, they call to confirm or cut the prep on the stone model — which is less accurate than an intraoral prep.
What’s the warranty on lab-fabricated RPDs?
Policies vary by lab. A typical warranty covers defects in materials or fabrication (porosity, base fracture, clasp breakage under normal handling) for 90 days. Damage from patient mishandling, clinical adjustment errors, or changes in the patient’s anatomy (ridge resorption, tooth loss) are not covered. Confirm details at case submission.
Can a flexible partial denture be converted to a traditional framework?
Not directly. The flexible framework cannot support a rigid clasp or metal connector. If the patient wants a traditional RPD, a new impression and new framework are needed.
Why does my RPD feel tight after a few months?
Tissue resorption or abutment tooth movement can alter the fit. A hard or soft reline usually resolves the issue without a complete remake. If clasps are too tight, the lab can adjust retention or replace the clasp arm.