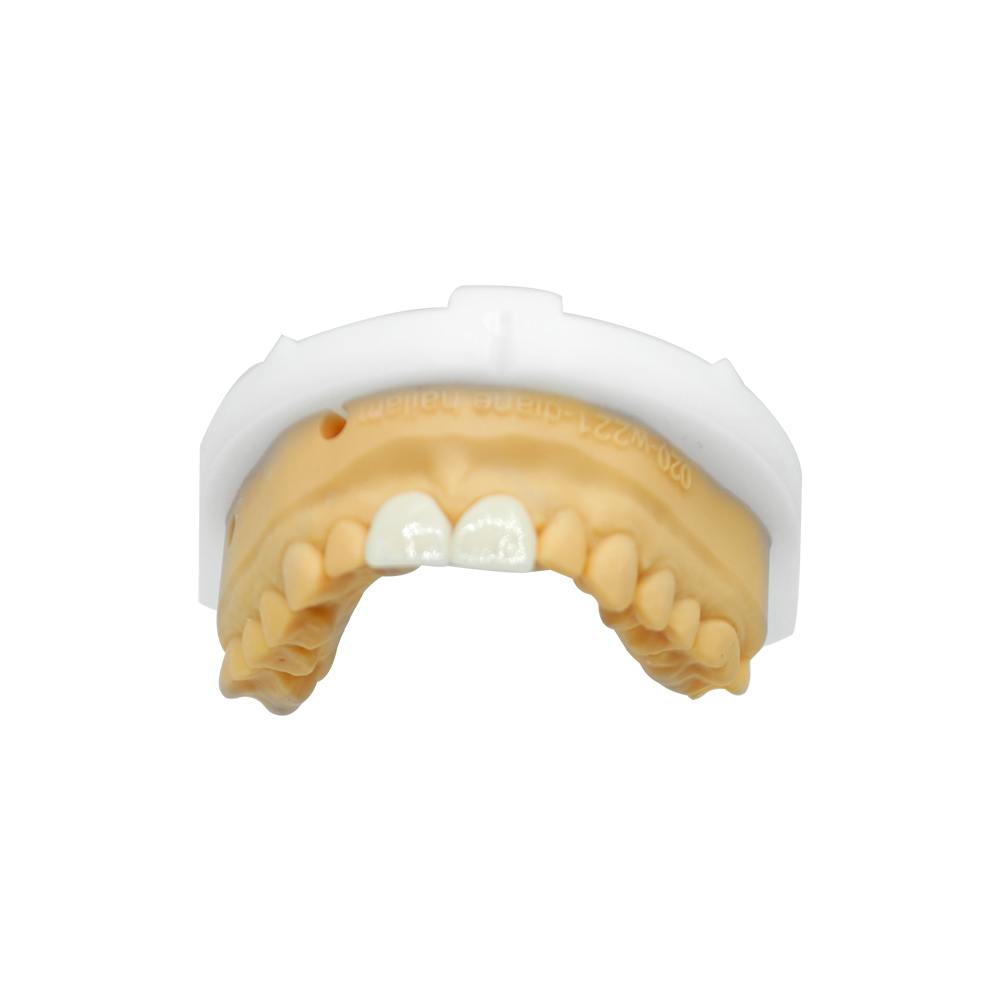
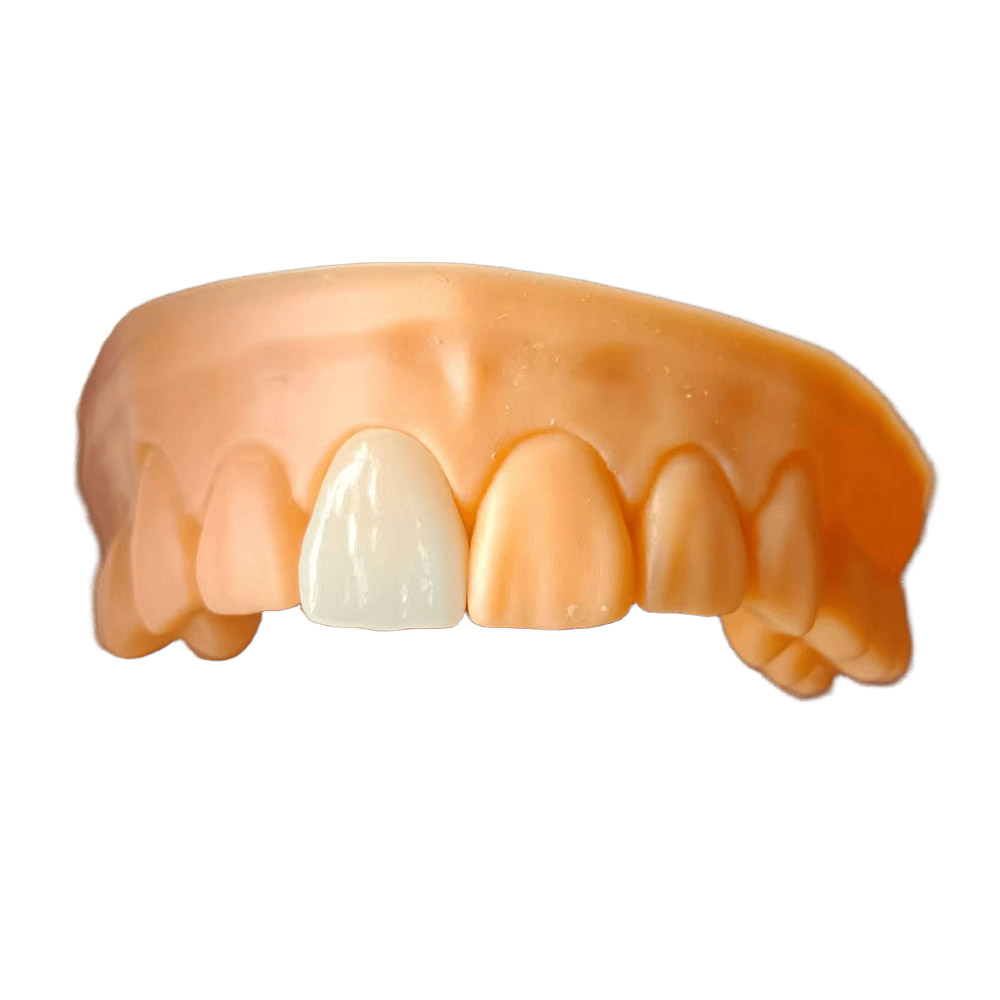
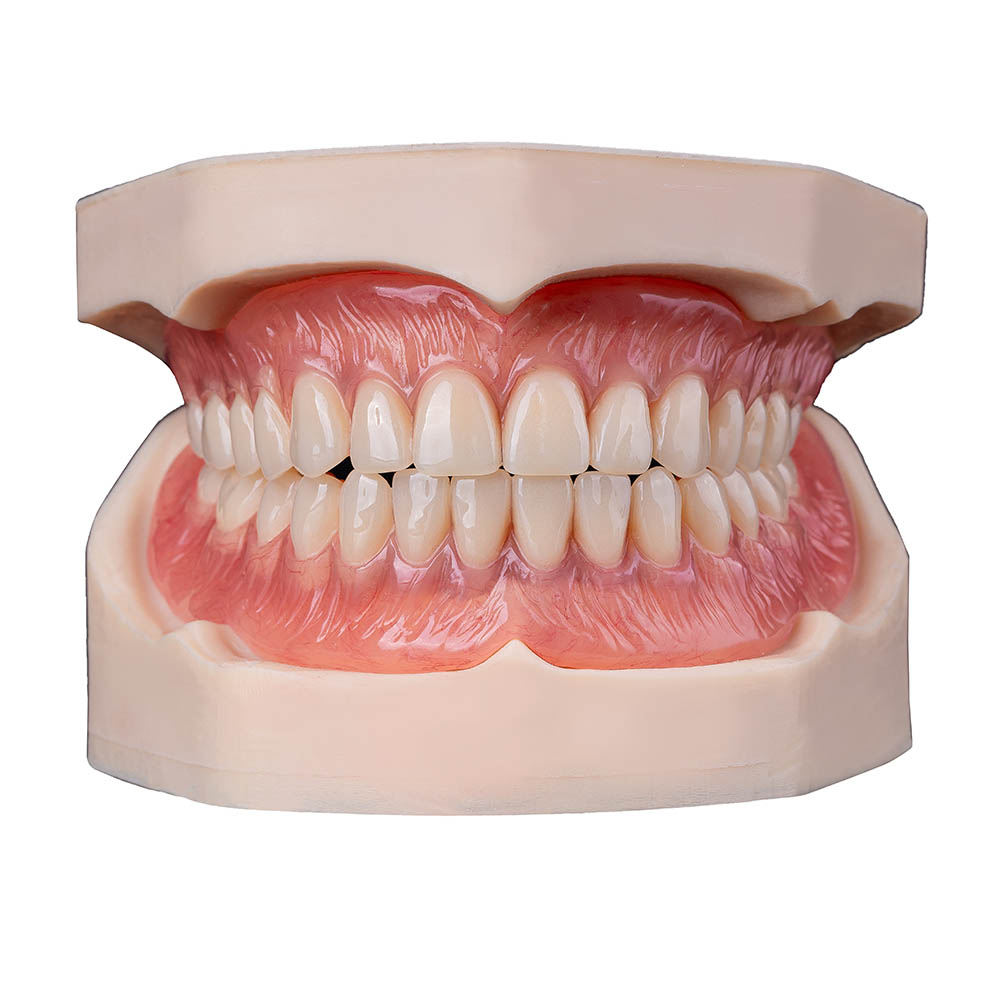
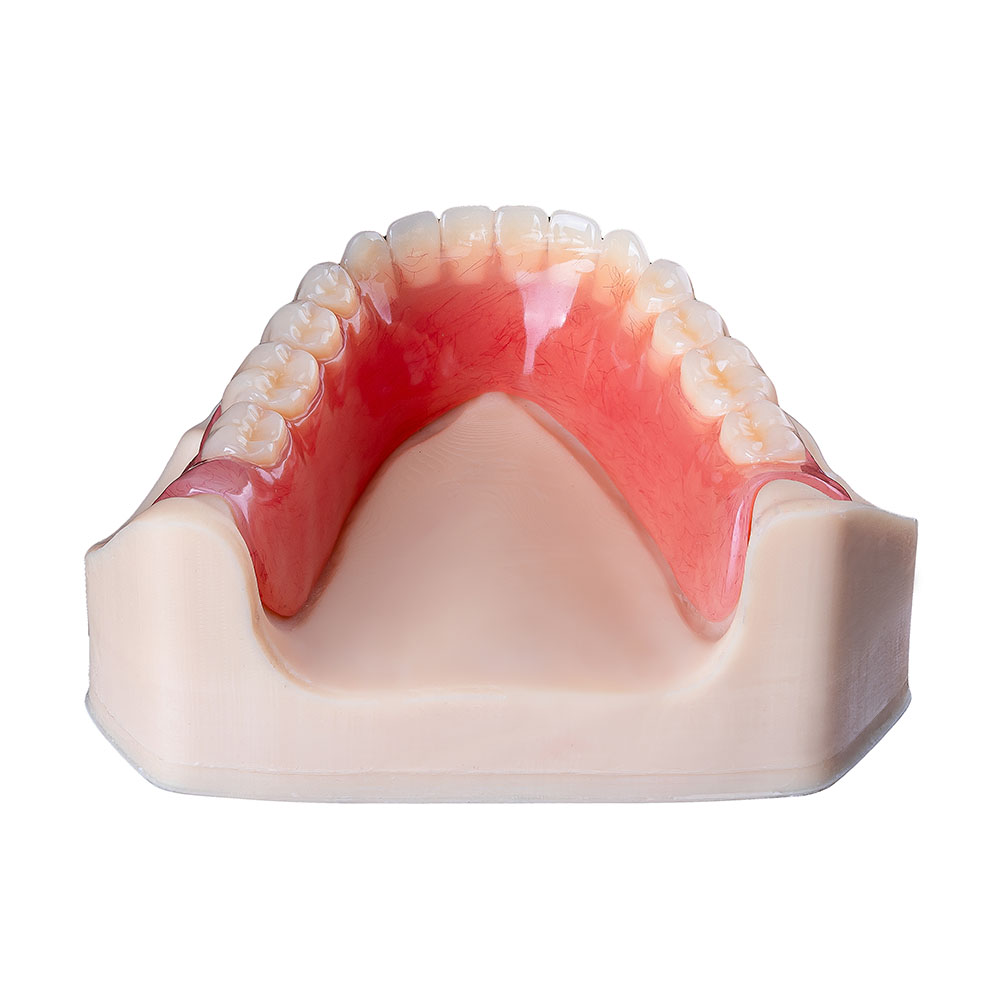
Single Complete Denture Cases Opposing Natural Teeth

🕢 [ Попълнете формуляра и ние ще ви отговорим в рамките на 30 минути! ]
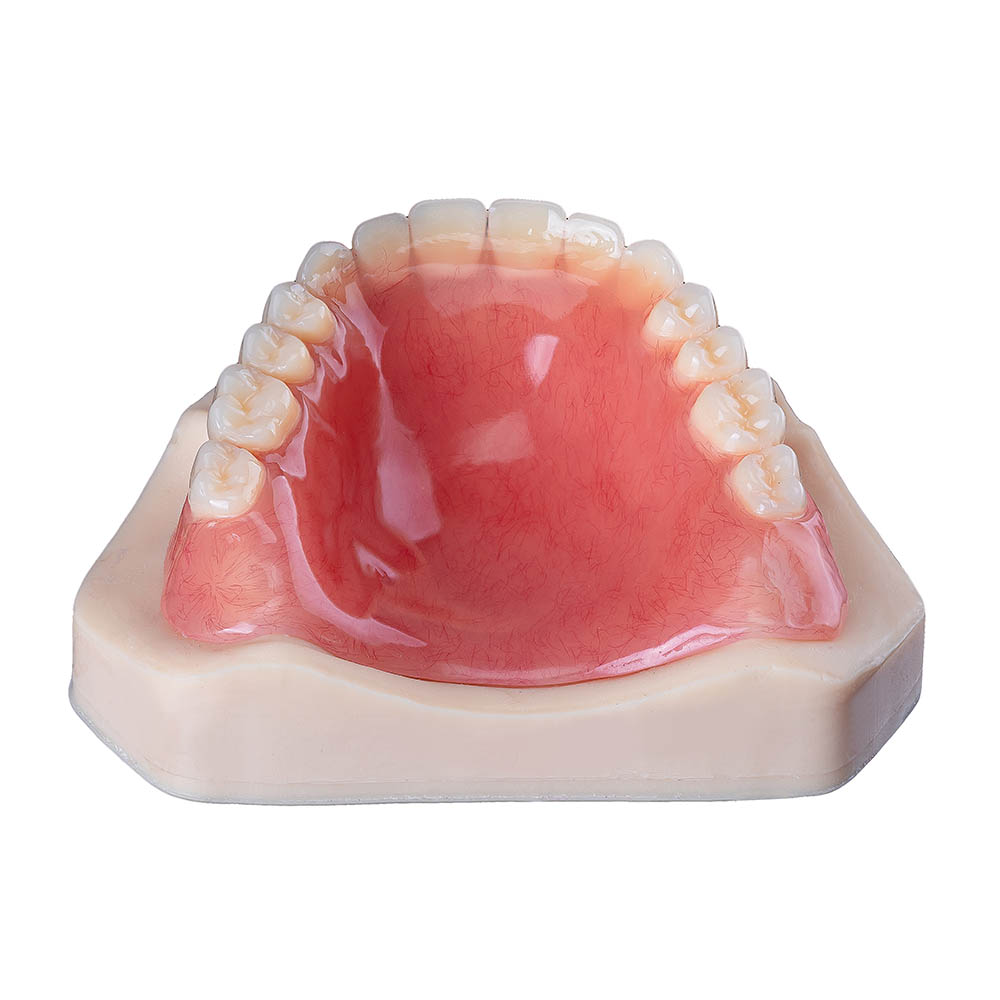
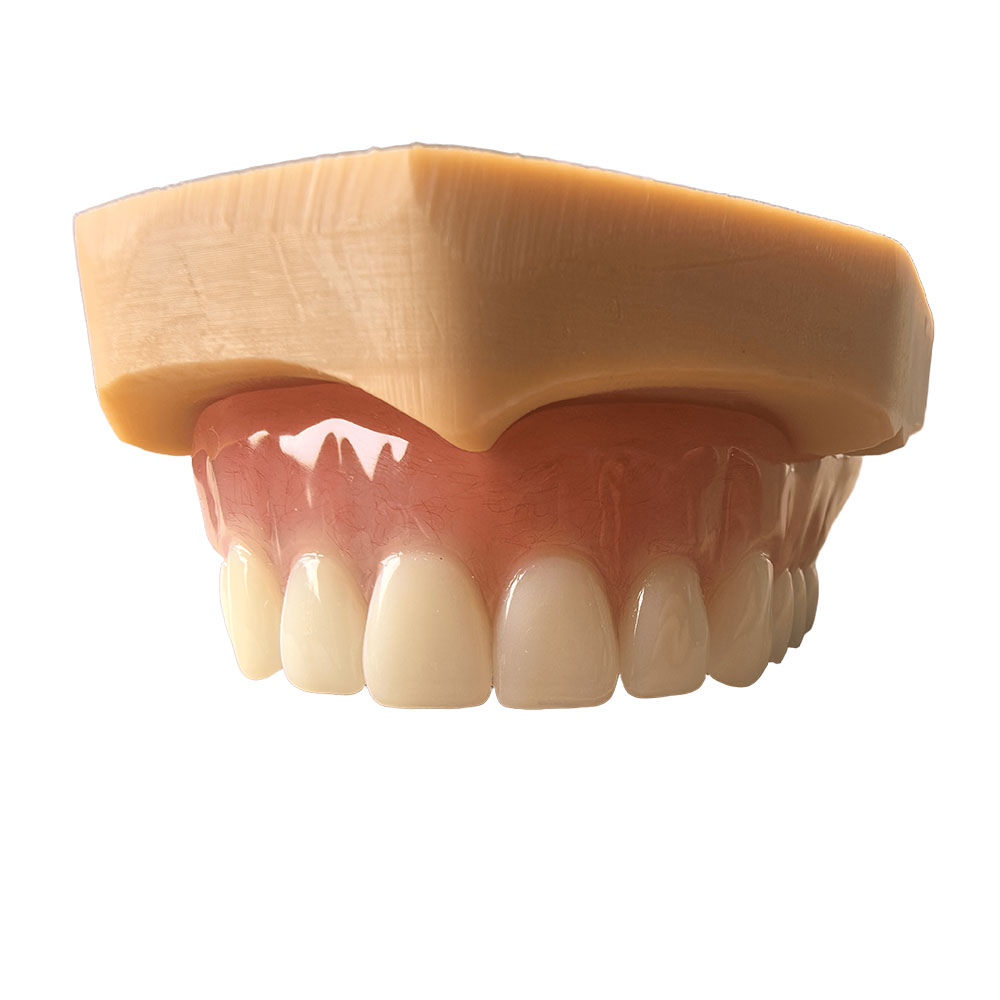
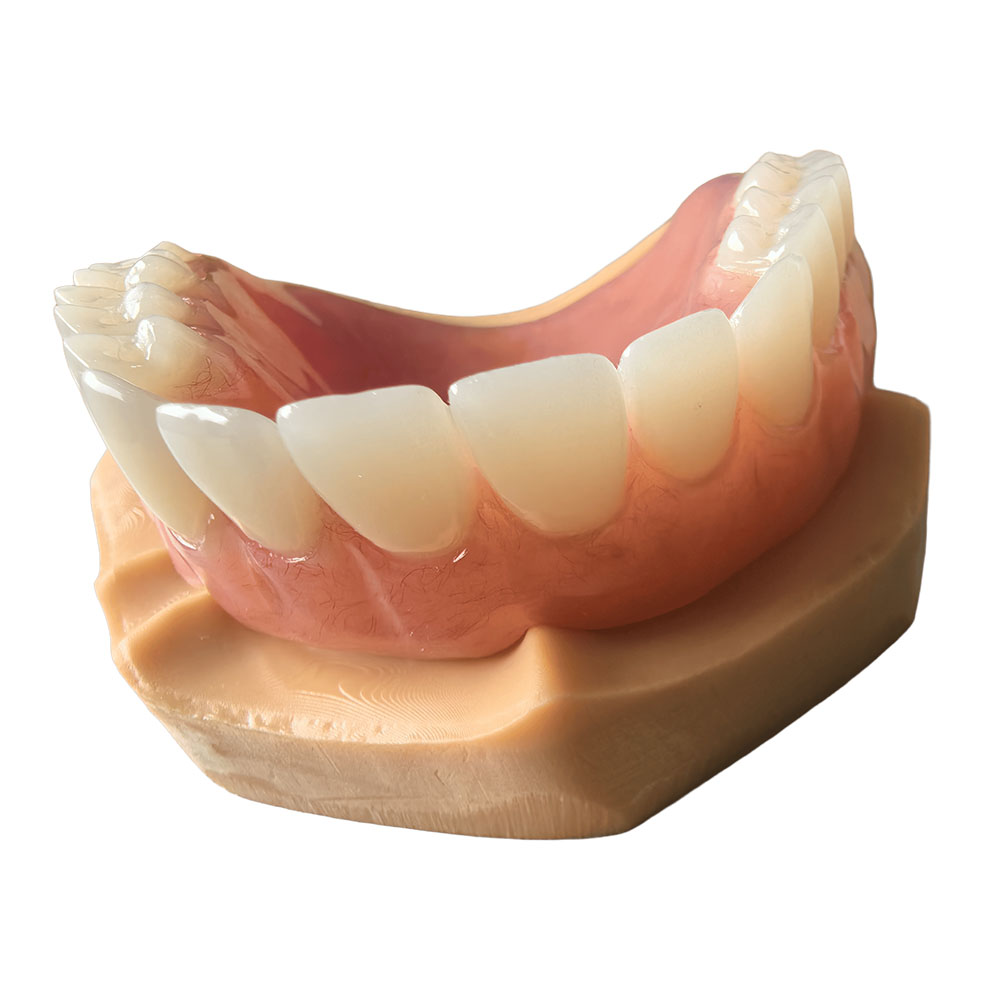
A maxillary complete denture that meets natural mandibular teeth is not a standard denture case. The lower anterior teeth keep erupting, the posterior region loses contact, and every bite drives force into the front of the upper ridge — where the bone is already thinnest. The clinical name for that pattern is combination syndrome, reported in roughly 24% of patients with natural mandibular anterior teeth opposing a maxillary complete denture.
ASD Dental Lab has fabricated these cases since 2012. Two parameters decide whether a single complete denture succeeds or comes back for a remake: how the work order addresses load distribution, and how the зъботехническа лаборатория holds vertical dimension through every step from CAD design to final QC.
Patient Presentation
A single complete denture opposing natural mandibular teeth presents with a clinical pattern that is consistent across the literature:
| Category | Подробности |
| Age & edentulism | Typically 65–80 years old; maxillary arch completely edentulous |
| Ridge condition | Significant resorption in the anterior maxilla; hyperplastic tissue overgrowth noted in some cases |
| Opposing dentition | Mandibular natural teeth present — anterior segment only; posterior occlusion lost |
| Chief complaint | Existing maxillary denture no longer stays in place during function; difficulty chewing and speaking clearly |
| Medical & financial constraints | Patient declined implant-supported overdenture due to cost and surgical limitations |
Why the Load Destroys the Ridge
Force imbalance drives the damage. With posterior occlusion gone, load concentrates on the anterior ridge, and yearly anterior maxillary bone loss of 0.43 mm (Kelly) and 0.32 mm/year (López-Roldán) has been measured in this configuration. Ellsworth Kelly described the condition in 1972.
Three mechanical problems compound each other:
- Concentrated anterior load → shearing forces on the anterior ridge accelerate resorption
- Resorption into a loosening cycle → lost ridge height opens space under the base, cutting retention further
- Occlusal plane distortion → supra-erupted lower anterior teeth flatten the plane, shrinking inter-arch space and disrupting neuromuscular balance
One principle governs every fabrication decision on a single complete denture: compressive forces are better tolerated by edentulous ridges than shearing forces. Base coverage and force distribution matter more than tooth aesthetics.
What the Doctor Specifies
A single complete denture work order needs to carry more than anatomy. Clinical requirements on the authorization:
- Impression method: Mucostatic (minimal pressure) technique to avoid displacing hyperplastic anterior tissue
- Maxillary relief: Strategic relief of the anterior palate to redirect pressure away from the resorbing ridge
- Balanced occlusion: simultaneous bilateral contact during lateral and protrusive movements, reducing forward-tipping force
- Vertical dimension maintenance: records taken on a semi-adjustable articulator to preserve existing VDO despite supra-eruption
- Pressure-indicating material verification: fit-checking paste at insertion to map contact distribution, with an adjustment protocol before final delivery
When natural anterior teeth supra-erupt and disrupt the occlusal plane, the doctor may specify DMLS (direct metal laser sintering) cobalt-chromium crowns. Acrylic denture teeth wear against natural enamel; DMLS offers superior strength, marginal adaptation, and long-term durability for restoring occlusal stability in single complete denture cases.
Follow-up runs 12 months, with mid-term reline evaluation when pressure distribution shows concentrated anterior contact.
Lab Execution
The single complete denture workflow sits at the intersection of three disciplines: removable prosthodontics, occlusion management, and fixed restorative work on the opposing arch.
| Clinical obstacle | Doctor’s requirement | Lab execution protocol |
| Economic & surgical limits | Patient cannot afford implants; surgical placement not an option | Standard removable prosthesis workflow; no surgical guide or implant components |
| Severe anterior ridge resorption | Mucostatic impression; anterior palatal relief | CAD: reduce base contact in anterior palatal zone; increase posterior palatal seal width to compensate |
| Supra-erupted mandibular anteriors | Maintain current VDO; do not arbitrarily increase | Design: semi-adjustable articulator; VDO transferred directly from facebow record |
| Force imbalance | Balanced occlusion across all excursions | Milling: simulate protrusive & lateral movements; adjust cusp angles for simultaneous contact |
| Denture tooth wear against natural enamel | DMLS Co-Cr crowns on mandibular anteriors when indicated | Fabricated in-house, shipped with the denture; dentist cements chairside before insertion |
| Objective pressure verification | Pressure-indicating paste at delivery | Fit-checking paste sample and contact map of expected high-contact zones included |
| Long-term maintenance | 12-month follow-up; interim reline if needed | Pre- and post-insertion full-arch scans archived; VDO record kept for future reline reference |
In-house production covers the whole case. DMLS components are designed, milled, sintered, and finished in our Shenzhen facility by the same team handling the single complete denture, so the occlusal registration carries across components without a vendor handoff.
Delivery Package
A single complete denture case ships with:
- Pressure-indicating paste and an illustrated adjustment protocol
- DMLS crowns when specified, shipped uncemented for chairside placement after final try-in
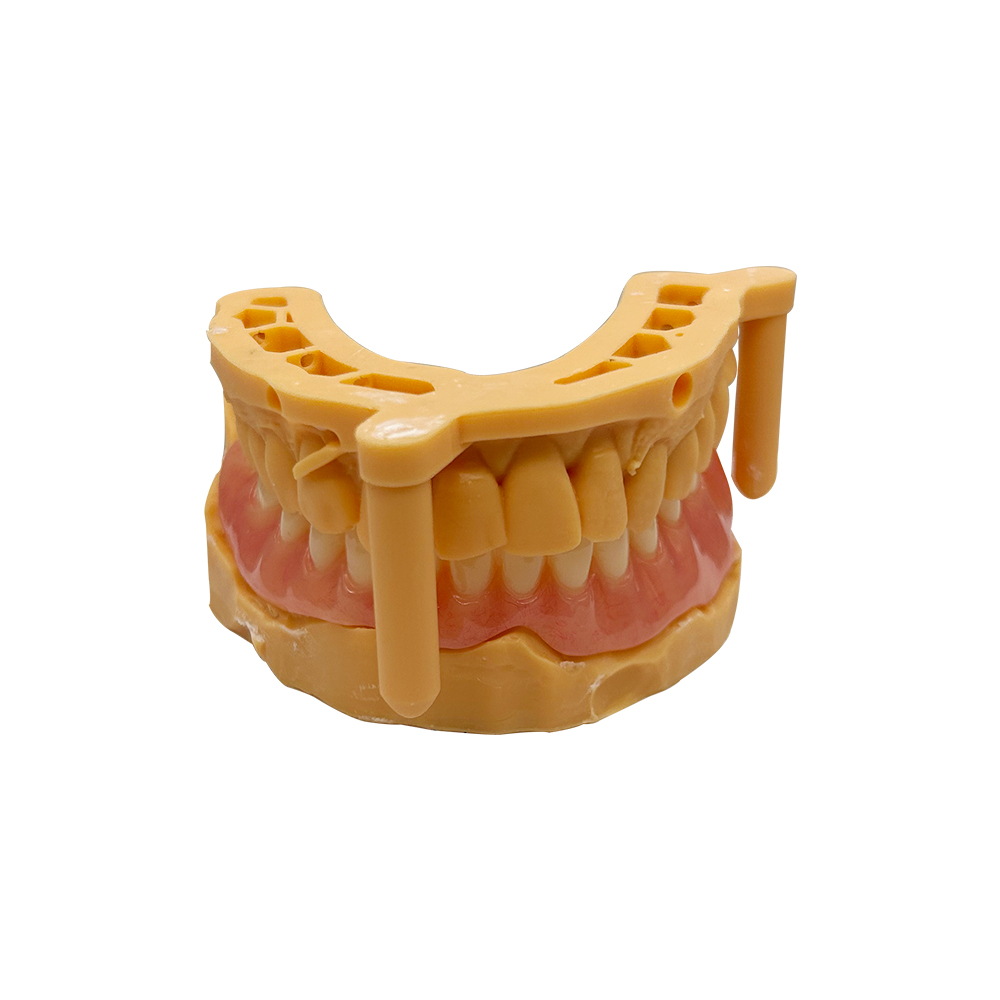
- Digital records: STL files of the master cast, articulator-mounted setup, and finished prosthesis, retained for future service
Published 12-month follow-ups on this approach report no complications, stable ridge morphology, and patients resuming normal diet including fibrous vegetables and moderately tough proteins. Authors attribute the outcome to optimized force distribution and minimized anterior ridge pressure, which they note can provide long-term stability for patients with financial or surgical limitations.
Why Single Complete Denture Cases Come Back
Prescriptions that name only anatomy. “Balanced occlusion” is the floor, not the goal. Without a specified relief zone and a verification method, the lab builds to average anatomic norms that don’t account for combination syndrome mechanics. A single complete denture authorized as a routine upper plate ends up with no way to verify where the load went.
Acrylic teeth against natural enamel. They wear flat within months, the occlusal plane shifts, load returns to the front of the base, and the resorption-loosening cycle restarts. DMLS crowns or high-impact composite buildups belong in the treatment plan whenever supra-eruption is present.
Split production is the quiet killer. When the opposing-arch work goes to a separate crown shop and the single complete denture to a removables department that doesn’t talk to the crown team, the occlusal registration won’t transfer cleanly. A зъботехническа лаборатория running in-house CAD, milling, sintering, and finishing lets one technician see both components on the same articulator before anything ships.
Service Commitment
For single complete denture cases opposing natural teeth, ASD Dental Lab includes:
- Pre-fabrication case review: design team evaluates impression and bite records within 24 hours of receipt. Registration errors or insufficient relief get flagged to the prescribing office before CAD work starts.
- Pressure-verification materials: every case ships with fit-checking paste and a contact map showing the expected distribution for a correctly seated prosthesis.
- Archived digital records: master cast, wax try-in setup, and finished denture stored 5 years. A reline or remake can reference the original VDO and occlusal scheme without a full re-impression.
- Remake policy: complete refabrication within 90 days of insertion due to a fabrication error — incorrect tooth mold, base fracture, or occlusal interference not attributable to impression defects — is remade at no cost to the зъботехническа лаборатория‘s client. Adjustments arising from tissue remodeling or patient adaptation are normal clinical events handled by the referring practice.
Records to Send for a Single Complete Denture Case
Sending complete records up front is what keeps a single complete denture on schedule. Any one of the following missing items will delay CAD work:
| Item | Why we need it |
| Final impression (irreversible hydrocolloid or PVS) | Captures tissue detail; mucostatic technique preferred for resorbed ridges |
| Opposing arch impression or model | Needed to mount on articulator and program excursive movements |
| Bite registration (centric relation record) | Establishes vertical dimension and horizontal jaw relationship |
| Facebow transfer (optional but recommended) | Improves mounting accuracy; critical for uneven ridge cases |
| Tooth shade & mold selection | Shade guide under natural light; specify mold size or send a photo of the patient’s original anterior teeth if available |
| Relief or design modifications | Example: “relieve anterior palate 0.5mm,” “extend posterior border to vibrating line,” “balanced occlusion required” |
| Opposing natural teeth status | Are they being restored? Send the crown design or at minimum the occlusal surface contour |
Digital files are accepted in .STL, .PLY, and .OBJ. The design team works in exocad, 3Shape, and Meshmixer.
In-House Capacity
Single complete dentures opposing natural teeth sit where removable prosthodontics, occlusion management, and fixed restorative work on the opposing arch overlap. Three departments carry a case of this type in a full-service dental lab:
- Digital design team (Shenzhen, ~100 CAD technicians) — denture base contours, virtual tooth setup, and opposing-arch crown or onlay design where applicable
- Milling department (~70 employees) — wax try-in models, final PMMA base, plus zirconia or DMLS components for the opposing teeth
- Finishing & QC (~120 employees) — hand-finished occlusal contacts, polishing, characterization, and final inspection with articulator remount to verify balanced contact
Roughly 460 employees across the Shenzhen and Huizhou facilities handle production in-house, with removable denture output around 4,000 cases per month in normal season and 6,500 at peak.
Свързани услуги
Patients with combination syndrome who start with a single complete denture opposing natural teeth often progress to implant-supported solutions when their financial or medical situation changes:
- Implant-retained overdentures (bar-supported or locator attachments)
- Hybrid prostheses (fixed-removable designs for fully edentulous arches)
- CAD/CAM custom abutments и zirconia screw-retained crowns for All-on-X cases
Immediate dentures and transitional partials are available when extraction sequencing is part of the treatment plan. The College of Prosthodontists position statement on denture replacement frequency sets out the clinical factors behind the reline-versus-remake decision.
Case questions and work orders go to our case management team, shipping to dental practices, клиники, и partner laboratories across North America, Europe (Netherlands, Germany, France, Belgium, UK, Austria), and other international markets.